Root cause analysis (RCA) is a structured method for finding the fundamental, system-related reasons an incident, near miss or problem occurred, so that corrective actions fix the underlying failure rather than just the visible symptom. In workplace safety, RCA moves an investigation past "what happened" to "why it was allowed to happen."
RCA is used after injuries, property damage, process upsets, quality failures and audit findings. Done well, it produces specific corrective actions that make the same type of event less likely to happen again anywhere in the organization.
What Is Root Cause Analysis (RCA)?
In a joint fact sheet, OSHA and the EPA define a root cause as "a fundamental, underlying, system-related reason why an incident occurred that identifies one or more correctable system failures." The same OSHA fact sheet on root cause analysis notes that an incident can have more than one root cause, and that correcting only an immediate cause may eliminate a symptom of a problem, but not the problem itself.
RCA is not a single technique. It is an approach that uses tools such as the 5 Whys, cause-and-effect diagrams, timelines and fault trees to trace a chain of events back to weaknesses in management systems: procedures, training, design, maintenance, staffing, supervision or resource decisions.
Immediate, Contributing and Root Causes
- Immediate cause: the condition or action that directly led to the event, often an unsafe act or unsafe condition, such as oil on a walkway.
- Contributing causes: factors that made the event more likely or more severe, such as poor lighting or time pressure.
- Root cause: the system failure that, if corrected, would prevent recurrence. In OSHA's oil spill example, the root cause may be an ineffective inspection and repair program that should have detected and stopped the leak.
Why Root Cause Analysis Matters
Stopping an investigation at "employee error" or "worker was not careful" rarely prevents the next incident. OSHA's incident investigation guidance stresses that investigations focusing on root causes, not on finding fault or blame, are more effective and also improve morale and productivity.
RCA also has a regulatory role. OSHA's Process Safety Management standard, 29 CFR 1910.119(m), requires employers to investigate each incident that resulted in, or could reasonably have resulted in, a catastrophic release of a highly hazardous chemical, and to document the factors that contributed to it. The EPA Risk Management Program at 40 CFR Part 68 has similar incident investigation requirements. ISO 45001 also requires organizations to evaluate the causes of incidents and nonconformities and determine whether similar issues exist elsewhere.
Common Root Cause Analysis Methods
OSHA's fact sheet lists brainstorming, checklists, logic or event trees, timelines, sequence diagrams and causal factor determination as useful tools, and recommends combining them. Widely used methods include:
5 Whys
The team asks "why?" repeatedly, usually about five times, until it reaches a cause that management can correct. It is quick and works well for simple events, but it can follow a single path and miss parallel causes if used alone.
Fishbone (Ishikawa) Diagram
A cause-and-effect diagram groups possible causes into categories such as people, methods, equipment, materials, environment and management. It helps teams brainstorm broadly before narrowing down.
Timeline and Causal Factor Charting
The team builds a sequence of events and conditions leading up to the incident, then identifies the causal factors at each step. This is especially useful when many people, shifts or systems were involved.
Fault Tree and Event Tree Analysis
Logic trees map how combinations of failures can produce an outcome. They are common in complex process safety investigations, where several safeguards must fail at once.
How to Conduct a Root Cause Analysis Step by Step
- Secure the scene and respond. Provide care, make the area safe and preserve evidence such as equipment, photos and records.
- Form the team. Include a trained facilitator, a supervisor or manager, and frontline employees who know the task. Involving workers improves both accuracy and trust.
- Gather facts. Interview witnesses separately and promptly, collect documents such as procedures, training records, maintenance logs and permits, and note environmental conditions.
- Build the sequence of events. Create a timeline that shows what happened, in what order and what conditions existed.
- Identify causal factors. Mark each point where a different action or condition would have prevented the event or reduced its severity.
- Drill down to root causes. For each causal factor, ask why it existed and why it was not detected or corrected earlier, until you reach a correctable system failure.
- Develop corrective actions. Address each root cause with specific actions, owners and due dates, favoring stronger controls in the hierarchy of controls over reminders and retraining.
- Verify and share. Track actions to completion, check that they worked, and share lessons learned with other sites and shifts.
Root Cause Analysis Example
Consider a hypothetical case. A forklift operator strikes a pedestrian at a blind corner in a warehouse. The pedestrian suffers a bruised leg.
- Why was the pedestrian struck? The operator did not see them at the corner.
- Why not? High racking blocks the view, and the convex mirror at that corner was missing.
- Why was the mirror missing? It was knocked down two months earlier and never replaced.
- Why was it not replaced? The damage was reported verbally, but there was no system for logging and tracking facility repairs.
- Why were pedestrians at that corner at all? The layout had no separated walkway after a recent racking change, and the change was not reviewed for traffic hazards.
Two root causes emerge: no system to track hazard repairs, and no review of layout changes for traffic risk. Corrective actions might include designated pedestrian walkways and physical barriers, a repair request and tracking process, and a management of change review for future layout changes. Simply telling the operator to "be more careful" would have addressed none of these.
Root Cause Analysis vs. Incident Investigation
An incident investigation is the full process of responding to, documenting and learning from an event. RCA is the analytical core of that investigation, the part that determines why the event happened. RCA is also used outside incident response, for example to analyze recurring audit findings, equipment failures or trends in near miss reports. Its outputs typically feed a corrective and preventive action (CAPA) process.
Common RCA Mistakes to Avoid
- Stopping at human error: people make mistakes, so ask why the system allowed the mistake to cause harm.
- Blame-focused interviews: workers who fear discipline share less information, which weakens the analysis.
- Jumping to solutions: deciding on a fix before the facts are gathered.
- Weak corrective actions: relying only on retraining, memos or "reinforce the procedure."
- No follow-up: closing actions without checking whether they were effective.
- Skipping near misses: waiting for an injury before analyzing a known problem.
How SMS360 Helps
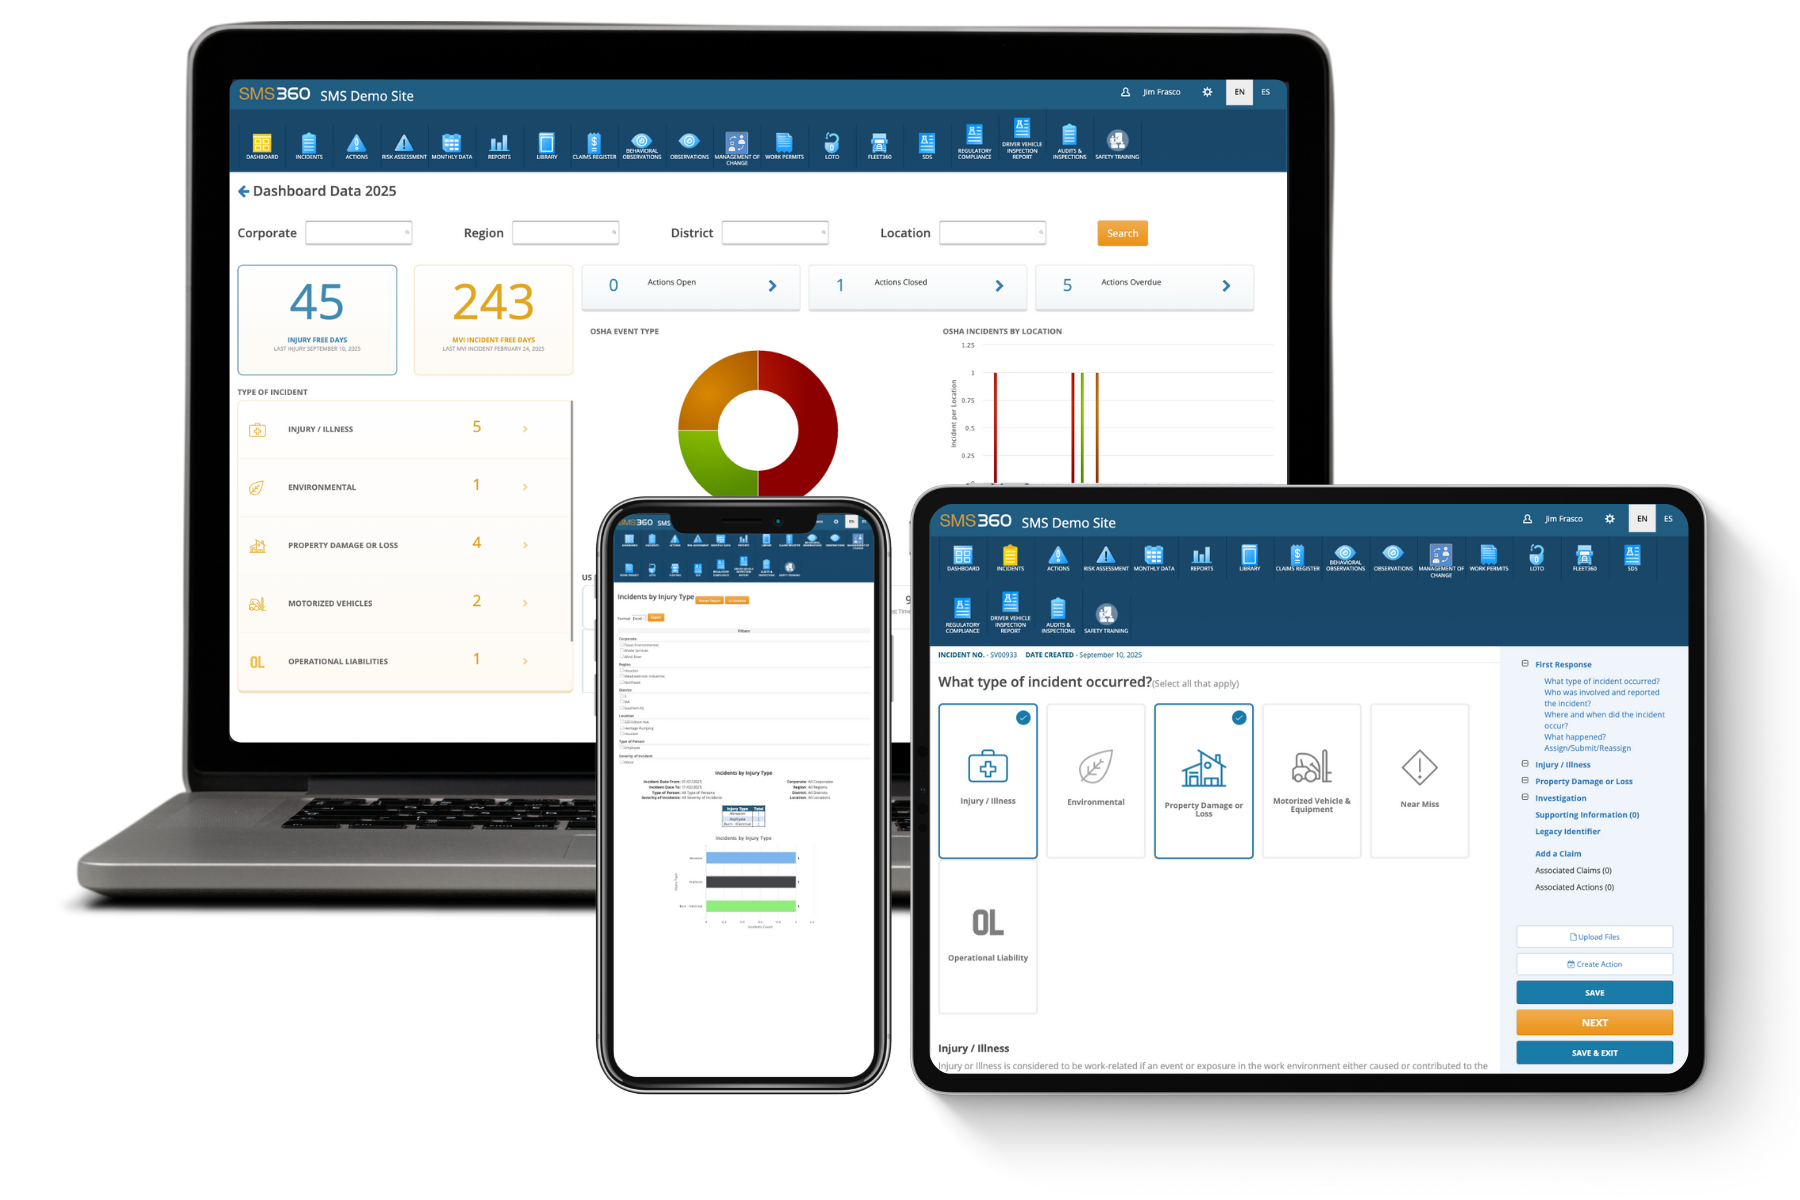
SMS360's Incident Management module gives investigation teams a structured place to record incident details, document findings and capture root causes. Corrective actions can be assigned to owners with due dates and reminders, and their status tracked until closure. Incident records and dashboards make it easier to spot repeat causes across sites and confirm that actions were completed.
Frequently Asked Questions
What is the purpose of root cause analysis?
The purpose of root cause analysis is to identify the underlying system failures that allowed an incident or problem to occur, so the organization can correct them and prevent recurrence. Instead of treating only the immediate cause, such as a spill or an unsafe act, RCA looks at procedures, training, design, maintenance and management decisions that made the event possible.
What are the most common root cause analysis tools?
Common RCA tools include the 5 Whys, fishbone (Ishikawa) diagrams, timelines, causal factor charting, checklists and fault or event trees. OSHA recommends combining tools: brainstorming and checklists may be enough for simple incidents, while complex incidents benefit from logic trees supported by timelines and sequence diagrams.
Is root cause analysis required by OSHA?
OSHA has no general standard requiring root cause analysis for every incident. However, the Process Safety Management standard, 29 CFR 1910.119(m), requires investigation of incidents that resulted in, or could reasonably have resulted in, a catastrophic release, including the factors that contributed. OSHA strongly encourages root cause analysis for all incidents and near misses as part of an effective safety program.
How many root causes can an incident have?
An incident can have more than one root cause. Most serious events result from several system weaknesses combining, such as a missing safeguard, an outdated procedure and production pressure. A good root cause analysis identifies each correctable system failure and assigns a corrective action to every one, rather than stopping at the first cause found.